Dissolving dermal fillers
One of the practical advantages of hyaluronic acid dermal fillers is that they can be dissolved. An enzyme called hyaluronidase breaks down hyaluronic acid, and injecting it into a treated area removes the filler.
This matters for two quite different reasons: it gives people a way out of a result they are unhappy with, and it is the emergency treatment for the most serious complication of filler injection.
How it works
Hyaluronidase is an enzyme that breaks the chemical bonds holding hyaluronic acid gel together. Injected into or around the filler, it breaks the product down into fragments the body clears naturally.
The effect begins quickly — often visible within 24 to 48 hours — and continues to settle over the following days to a couple of weeks. More than one session is sometimes needed, particularly with firmer, more cross-linked products or where a large volume was placed.
Hyaluronidase is a prescription medicine. It must be prescribed by a doctor after a consultation, and Australian law restricts what can be published about prescription medicines.
What can and cannot be dissolved
- Hyaluronic acid fillers can be dissolved. These are the most commonly used fillers in Australia today.
- Non-hyaluronic acid fillers cannot. Calcium hydroxylapatite, poly-L-lactic acid, polymethylmethacrylate and silicone are not affected by hyaluronidase. Removing those, where it is possible at all, may require surgery.
- Permanent fillers are the hardest problem. This is the single strongest practical argument for using a reversible product in the first place.
If you do not know what was injected, say so at consultation — the record from the original treatment matters, and where it is unavailable, imaging such as ultrasound can sometimes help identify what is present.
The emergency use: vascular occlusion
The most serious complication of dermal filler is vascular occlusion — filler entering or compressing a blood vessel and blocking blood supply. Untreated, this can cause tissue death and, where vessels supplying the eye are involved, permanent vision loss.
Hyaluronidase is the treatment, and it is time-critical — the sooner it is given, the better the outcome. This is why any practitioner injecting hyaluronic acid filler should have hyaluronidase immediately available in the room, and why it is a fair question to ask before treatment.
What it looks and feels like
Worth knowing in advance, because recognising it early is the whole game and it can begin during the treatment or hours afterwards.
- Pain that is severe, or out of proportion to what you were told to expect — and particularly pain that is increasing rather than settling. Filler treatment is briefly uncomfortable; it should not hurt more an hour later than it did at the time.
- Blanching — an area of skin that goes noticeably pale or white, sometimes immediately.
- A mottled, net-like or dusky discolouration developing over the following minutes to hours, often grey, purple or bluish.
- Any change in vision — blurring, a shadow, loss of part of the field, or double vision. This is the emergency within the emergency.
- Severe pain around the eye or forehead, or a headache that is new and severe.
- Later: blistering, crusting or an area that looks like it is breaking down.
What to do
Do not wait to see whether it settles. That is the single most important sentence on this page. Every hour matters, and the outcome of vascular occlusion is far better when it is treated early.
- Ring us that treated you immediately, at any hour, and say what you are experiencing in those words.
- If you cannot reach them, go to an emergency department — and tell them you have had dermal filler, when, where on the face, and that you are concerned about vascular occlusion. Use that phrase; it is the one that moves things.
- For any change in vision, go straight to an emergency department. Do not drive yourself.
- Take whatever record you have of what was injected and where.
Nobody will think you overreacted. This is a complication where being wrong costs an appointment and being right costs tissue or sight.
What to ask before you ever have filler
- Is hyaluronidase in the room? Not in the building, not orderable — in the room, in date.
- Who is injecting, and what are their qualifications?
- Is the product hyaluronic acid, and therefore reversible?
- Who do I ring after hours if something is wrong, and will someone answer?
- What are the signs you want me to call about? A practitioner who answers that fluently has thought about it.
Why people have filler dissolved
- An unsatisfactory result — too much volume, an unnatural shape, or a change they no longer want.
- Asymmetry that has not settled.
- Lumps or nodules, including ones that appear months after treatment.
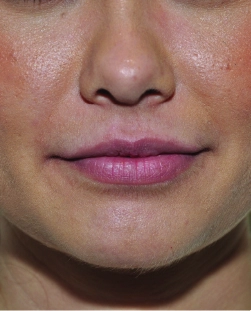
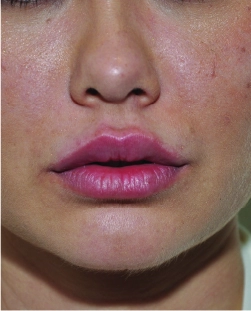
- Migration — product that has moved from where it was placed. This is most commonly seen around the lips, where it can produce a shelf above the lip border.
- Tyndall effect — bluish discolouration where filler sits too superficially, most often under the eyes.
- Delayed inflammatory reactions, sometimes triggered by illness or vaccination.
- Accumulated filler over many years, where repeated treatment has changed the shape of the face more than intended. Dissolving and starting again is a legitimate approach.
- Before surgery, where filler would complicate a planned procedure.
How to tell whether your lip filler has migrated
The commonest reason people come in for dissolving, and one you can largely assess yourself.
Lips have a natural border — the slightly raised ridge where the lip meets the skin of the face. Filler is meant to stay inside it. When product moves beyond that border, the result is a shelf of fullness sitting above the lip rather than in it.
- Look with your lips relaxed and closed, not smiling. Does the fullness extend past the natural border onto the skin above the upper lip?
- Look for the philtrum — the two ridges running from the nose to the centre of the upper lip. Migration commonly flattens them.
- Feel it. Run a clean fingertip along the border. A firm, slightly raised band above the lip line, distinct from the lip itself, is the thing being described.
- Check in profile. Migration often reads more obviously from the side than from the front.
- Compare with an old photograph from before any treatment, which is the only reliable version of your own border.
Two things worth knowing. Migration is not always the result of poor technique — repeated treatment over years, large volumes, and the natural movement of a mobile area all contribute. And adding more filler to disguise it makes it worse, which is the loop most people are in by the time they come in.
Why superficial filler looks blue
The Tyndall effect has a straightforward explanation, and it is the same physics that makes a vein under the skin look blue when the blood inside it is not.
When filler gel sits too close to the surface, light hitting it is scattered — and shorter, bluer wavelengths scatter more than longer, redder ones. What reaches your eye from that spot is therefore shifted toward blue. The gel is clear; the blue is an optical effect of where it is sitting.
It shows most under the eyes, where the skin is thinnest, and it does not fade on its own. Dissolving is the reliable answer.
How the appointment runs
- Consultation with a doctor, because hyaluronidase is a prescription medicine. What was injected, when, how much, where, and by whom — all of it matters.
- Examination, including how the area moves and where the product actually sits, which is not always where it was placed.
- A skin test beforehand in some cases, because allergy to hyaluronidase is a recognised risk.
- The treatment, which is quick — a series of small injections into and around the product.
- The wait. Swelling can be pronounced for several days and makes the result impossible to judge early. Most of the change is apparent within 24 to 48 hours; settling continues for up to a couple of weeks.
- Review, and a further session if the product has not fully cleared.
- A gap before any new filler, so the area settles and residual hyaluronidase is no longer active.
Bring whatever records you have — product name, volume, areas, dates, who performed it. If you have none, say so plainly rather than guessing; a wrong answer is worse than no answer.
What to expect
The treatment itself is quick. Expect some redness, swelling and possible bruising at the injection sites, generally settling within a few days. Swelling can be pronounced initially and can make it hard to judge the result for several days.
Once swelling settles, the treated area returns toward its pre-filler state. It is worth being clear-eyed about this: dissolving filler in a face that has aged since the filler was placed reveals the face as it is now, not as it was then. Some people find that confronting, and it is better to expect it.
Where a further filler treatment is planned, practitioners usually wait a period after dissolving before re-treating, so the area has settled and residual hyaluronidase is no longer active.
One more expectation worth setting: dissolving is not always a single, clean subtraction. Where product has been in place a long time, has migrated, or sits in several planes, the area can look uneven for a week or two as different parts clear at different rates. That usually resolves; occasionally it needs a second session to even out.
Who this comes up for
Anyone unhappy with a recent result. A legitimate reason on its own, and you do not need to justify it beyond saying so. Waiting a fortnight first is usually sensible, because swelling accounts for a good deal of early dissatisfaction.
Long-term filler patients. The group most often surprised. Product placed repeatedly over years accumulates, and the face changes shape gradually enough that nobody notices until a photograph does. Dissolving everything and starting from an honest baseline is a recognised and reasonable approach.
Anyone with a lump that has appeared months or years later. Delayed nodules are a recognised phenomenon, sometimes triggered by an illness or a vaccination. They need assessment rather than assumption — not every lump in a treated area is filler.
Anyone who does not know what was injected. Common, particularly where treatment was had overseas or the clinic has closed. It changes the plan rather than preventing it.
Anyone who has had a permanent or semi-permanent filler. Hyaluronidase will not touch it, and that is worth establishing before an appointment is booked rather than after.
Before planned surgery. Tell your surgeon what has been injected and when, regardless of whether you think it is relevant.
What sits outside this
- We cannot dissolve non-hyaluronic-acid fillers. Hyaluronidase has no effect on them.
- We do not dissolve on the basis of a guess about what was injected without assessing first.
- We do not administer hyaluronidase without a doctor’s consultation and prescription.
- We do not add filler to disguise migration.
- We do not promise a return to how your face looked before the filler was placed — time has passed, and the face underneath has changed.
What you should leave with
- A record of what was dissolved, where, and how much hyaluronidase was used
- What to expect over the next fortnight, including that swelling makes early judgement unreliable
- Whether a second session is likely
- How long before any new filler could be considered
- Written aftercare, and the specific signs to call about
- An itemised quote covering the possibility of more than one session
Risks
- Pain, redness, swelling, bruising and tenderness at injection sites
- Allergic reaction, including rarely anaphylaxis — hyaluronidase is derived from animal or recombinant sources and allergy is a recognised risk. A skin test is sometimes used beforehand
- Infection
- Dissolving more than intended, including some of the body’s own hyaluronic acid in the surrounding tissue, which can leave the area looking temporarily hollow or lax before it recovers
- Incomplete dissolving, requiring further sessions
- An unsatisfactory appearance after dissolving
- No effect, where the product injected was not hyaluronic acid
Please read our information on the risks and complications of cosmetic surgery before proceeding.
Expected, versus call us, versus seek urgent care
- Expected: redness, swelling that can be pronounced for a few days, bruising, tenderness, and an area that looks flatter or slightly hollow before it settles.
- Call us: swelling that is increasing after several days, a lump that is not settling, spreading redness or heat, pus or fever, or an appearance you are unhappy with once the swelling has gone.
- Seek urgent medical attention: difficulty breathing, widespread rash, or swelling of the lips, tongue or throat — which may indicate an allergic reaction.
Cost and consultation
Cost depends on the amount of product to be dissolved, the areas involved and whether more than one session is needed, and is quoted at consultation. As at September 2024 and including GST, a consultation with a Cosmetic Doctor is $150.
Bring whatever records you have of the original treatment — product, volume, areas, date and who performed it. It genuinely changes the assessment.
Cosmetic treatment is not covered by Medicare, and we are not a no-gap provider.
We are at 4 Burke Road, Malvern East VIC 3145, five minutes’ walk from Caulfield station. Phone 1300 852 050, or use the online consultation form.
Related: dermal filler treatments, filler before and after, risks of cosmetic treatments.
Common questions about dissolving dermal fillers
Can dermal filler be removed?
Hyaluronic acid filler can. An enzyme called hyaluronidase breaks the bonds holding the gel together, and the body clears the fragments.
How quickly does it work?
Often visibly within 24 to 48 hours, continuing to settle over the following days to a couple of weeks. More than one session is sometimes needed.
Which fillers cannot be dissolved?
Calcium hydroxylapatite, poly-L-lactic acid, polymethylmethacrylate and silicone. Removing those, where possible at all, may require surgery — which is the strongest practical argument for using a reversible product in the first place.
What if I do not know what was injected?
Say so plainly rather than guessing — a wrong answer is worse than no answer. Records from the original treatment matter, and where they are unavailable, imaging such as ultrasound can sometimes help identify what is present.
What is vascular occlusion?
Filler entering or compressing a blood vessel and blocking blood supply. Untreated it can cause tissue death and, where vessels supplying the eye are involved, permanent vision loss.
What does it look and feel like?
Severe or increasing pain out of proportion to expectations; blanching — skin going pale or white; a mottled, net-like or dusky discolouration over minutes to hours; severe new pain around the eye or forehead; and later, blistering or an area that looks like it is breaking down.
What is the most urgent sign?
Any change in vision — blurring, a shadow, loss of part of the field, or double vision.
What should I do?
Do not wait to see whether it settles. Ring us that treated you immediately, at any hour. If you cannot reach them, go to an emergency department and say you have had dermal filler and are concerned about vascular occlusion. For any change in vision, go straight to an emergency department and do not drive yourself.
What if I am wrong?
Nobody will think you overreacted. Being wrong costs an appointment; being right and waiting costs tissue or sight.
What should I ask before having filler at all?
Whether hyaluronidase is in the room and in date; who is injecting and with what qualifications; whether the product is hyaluronic acid and therefore reversible; who to ring after hours; and what signs they want you to call about.
Why do people have filler dissolved?
An unsatisfactory result, asymmetry, lumps or nodules, migration, the Tyndall effect, delayed inflammatory reactions, accumulated filler over many years, and before planned surgery.
How do I tell whether my lip filler has migrated?
Look with your lips relaxed and closed — does the fullness extend past the natural border onto the skin above the upper lip? Check whether the philtrum ridges have flattened, feel for a firm raised band above the lip line, look in profile, and compare with an old photograph.
Does migration mean bad technique?
Not necessarily. Repeated treatment over years, large volumes and the natural movement of a mobile area all contribute.
Can I fix migration with more filler?
No — adding more to disguise it makes it worse, and that is the loop most people are in by the time they come in.
Why does superficial filler look blue?
Light hitting the gel is scattered, and shorter, bluer wavelengths scatter more than longer ones — the same physics that makes a vein look blue when the blood inside it is not. The gel is clear; the blue is an optical effect of where it sits.
Does the blueness fade on its own?
No. Dissolving is the reliable answer.
Does a doctor have to do it?
Yes. Hyaluronidase is a prescription medicine and must be prescribed by a doctor after a consultation.
Might I need a skin test?
Sometimes, because allergy to hyaluronidase is a recognised risk.
How will I look afterwards?
The area returns toward its pre-filler state — which is the face as it is now, not as it was when the filler was placed. Some people find that confronting, and it is better to expect it.
Will it be even straight away?
Not always. Where product has been in place a long time, has migrated, or sits in several planes, the area can look uneven for a week or two as different parts clear at different rates.
How long before I can have filler again?
Practitioners usually wait a period, so the area settles and residual hyaluronidase is no longer active.
I am unhappy with a result I had last week. Should I dissolve it now?
Waiting a fortnight first is usually sensible, because swelling accounts for a good deal of early dissatisfaction. After that, being unhappy is a sufficient reason on its own.
I have had filler for years. Should I start again?
Product placed repeatedly accumulates, and the face changes shape gradually enough that nobody notices until a photograph does. Dissolving everything and starting from an honest baseline is a recognised and reasonable approach.
I have a lump that appeared a year later. Is that filler?
Possibly — delayed nodules are recognised, sometimes triggered by illness or vaccination. But not every lump in a treated area is filler, so it needs assessment rather than assumption.
Should I tell a surgeon about past filler?
Yes, regardless of whether you think it is relevant — what was injected and when.
What are the risks?
Pain, redness, swelling, bruising and tenderness; allergic reaction including rarely anaphylaxis; infection; dissolving more than intended, including some of the body’s own hyaluronic acid, leaving the area temporarily hollow or lax; incomplete dissolving needing further sessions; an unsatisfactory appearance afterwards; and no effect where the product was not hyaluronic acid.
When should I seek urgent care after dissolving?
Difficulty breathing, widespread rash, or swelling of the lips, tongue or throat — which may indicate an allergic reaction.
What does it cost?
It depends on the amount of product, the areas involved and whether more than one session is needed, and is quoted at consultation. A Cosmetic Doctor consultation is $150 as at September 2024, including GST. Not covered by Medicare.
Individual results may vary. Any surgical or invasive procedure carries risks. Before proceeding you should seek a second opinion from an appropriately qualified health practitioner.
Images on This Page
-
https://www.meclinic.com.au/wp-content/uploads/2024/03/meclinic-logo.png
Me Clinic
-
https://www.meclinic.com.au/wp-content/uploads/2022/02/call.png
call
-
https://www.meclinic.com.au/wp-content/uploads/2022/03/dermalfillertreatments-lips-before-250x310-1.webp
(no alt text)
-
https://www.meclinic.com.au/wp-content/uploads/2022/03/dermalfillertreatments-lips-after250x310.webp
(no alt text)
-
https://www.meclinic.com.au/wp-content/uploads/2025/11/gordon-photo.png
(no alt text)
-
https://www.meclinic.com.au/wp-content/uploads/2025/11/daniel-photo.png
(no alt text)
-
https://www.meclinic.com.au/wp-content/uploads/2024/02/acps.png
(no alt text)
-
https://www.meclinic.com.au/wp-content/uploads/2024/02/racs.png
(no alt text)
-
https://www.meclinic.com.au/wp-content/uploads/2024/02/fracs.png
(no alt text)
-
https://www.meclinic.com.au/wp-content/uploads/2024/02/isaps.png
(no alt text)
-
https://www.meclinic.com.au/wp-content/uploads/2024/02/cpca.png
(no alt text)
-
https://www.meclinic.com.au/wp-content/uploads/2022/02/auscop.png
(no alt text)
-
https://www.meclinic.com.au/wp-content/uploads/2022/02/amav.png
(no alt text)
-
https://www.meclinic.com.au/wp-content/uploads/2022/03/channel7.png
(no alt text)
-
https://www.meclinic.com.au/wp-content/uploads/2022/03/channel9.png
(no alt text)
-
https://www.meclinic.com.au/wp-content/uploads/2022/03/channel10.png
(no alt text)
-
https://www.meclinic.com.au/wp-content/uploads/2022/03/abc.png
(no alt text)
-
https://www.meclinic.com.au/wp-content/uploads/2022/02/malvern-map-thumb.jpg
(no alt text)
-
https://www.meclinic.com.au/wp-content/uploads/2022/03/home-conctact-tab.jpg
(no alt text)
-
https://bat.bing.com/action/0?ti=56339805&Ver=2&mid=ab4de047-7ca4-4e36-ae55-f5484b7563d7&bo=1&sid=eeb9aee0ac3c11f1abd7c383d5051bc6&vid=eeb9c130ac3c11f1a3fe25452df9d5fb&vids=1&msclkid=N&pi=918639831&lg=en-US&sw=1280&sh=720&sc=24&tl=Volume%20Enhancing%20Treatments%20%7C%20Cheeks,%20Lips%20%26%20Jawline%20Contouring&p=https%3A%2F%2Fwww.meclinic.com.au%2Fface%2Fdermal-filler-treatments%2F&r=&evt=pageLoad&sv=2&cdb=AQAQ&rn=776622
(no alt text)