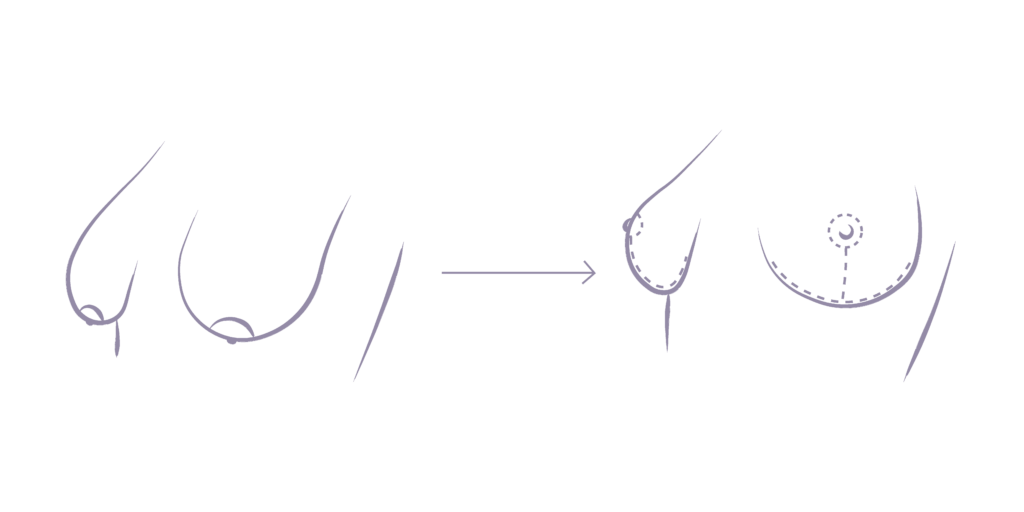Breast reduction and lift
A breast reduction and lift combines two procedures in one operation: reducing breast size by removing excess fat, glandular tissue and skin, and lifting the breast while repositioning the nipple and areola.
It is considered by people with large or sagging breasts who experience back, neck and shoulder pain, skin irritation beneath the breast crease, or limitation in physical activity. Because the reduction component is often performed for functional rather than purely cosmetic reasons, this is one of the procedures more likely to attract a Medicare rebate.
What the combined procedure addresses
- Back, neck and shoulder pain associated with breast size and weight.
- Skin irritation and rashes beneath the breast crease.
- Limitations on physical activity and exercise.
- Indentations from bra straps.
- Stretched skin, and nipples resting below the breast crease with enlarged areolas.
- Breast size, shape and position together.
- Asymmetry between the breasts.
The shape and size of your breasts before surgery influences both the procedure and the outcome. Outcomes vary depending on individual anatomy and skin quality, and individual results may vary.
Why combine rather than reduce alone
A reduction removes volume and weight. Where the breast has also lost position - the nipple resting below the breast crease, or the skin stretched by the weight it has carried - reducing volume alone can leave the breast lower and less supported than intended. Adding a mastopexy repositions the nipple and areola and removes the excess skin at the same time.
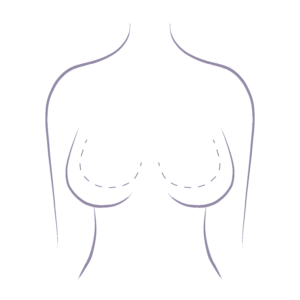
In many cases the two are performed together as a matter of course, since the incision patterns used for reduction (anchor or lollipop) are the same patterns used for a lift. Your surgeon assesses at consultation whether a lift component is needed in your case.
What the procedure involves
The procedure is performed under general anaesthesia in an accredited private hospital. The surgeon makes incisions - most commonly an anchor pattern where there is significant enlargement and sagging, or a lollipop pattern for moderate correction - removes excess fat, glandular tissue and skin, reshapes the remaining breast tissue, reduces the areola if required, repositions the nipple, and closes the incisions.
Because the procedure is more extensive than either component alone, an overnight hospital stay is common. Your surgeon will discuss this at consultation.
The record your assessment will rest on
This is the single most useful thing you can do before your appointments, and almost nobody arrives having done it. Whether a reduction is assessed as addressing a functional problem turns on evidence of symptoms over time, and on what has already been tried. A clear account written down beats a vague recollection under time pressure in a consulting room, and it is equally useful for your GP, your surgeon and your insurer.
The symptoms worth recording
- Shoulder grooving. Indentations left by bra straps. Note whether they are visible after the bra is removed, and how long they take to disappear.
- Neck, upper back and shoulder pain. Where it sits, how often, what makes it worse, and what you take for it.
- Rash or breakdown in the fold beneath the breast - intertrigo. Note how often it recurs, particularly in summer, and what you have used to treat it.
- Exercise and activity limitation. Be specific: which activities you have stopped, which you modify, and whether two bras or a particular support is needed to do them at all.
- Sleep and posture. Positions you can no longer sleep in, and whether you find yourself rounding your shoulders.
- Bra fitting. Whether you can buy your size in ordinary shops, and what a professional fitting concluded.
- Numbness or tingling into the arms or hands, if present.
- The effect on daily life - work, clothing, swimming, and what you avoid.
What has already been tried
Assessments give weight to conservative measures attempted before surgery. Record what you have done and for how long: a professionally fitted supportive bra, physiotherapy or a prescribed exercise program, over-the-counter or prescribed pain relief, topical treatment for rash in the fold, weight management where relevant, and any imaging, physiotherapy notes or specialist letters already on file.
Two practical points. First, the record is far more persuasive when it is dated and continuous - GP entries made over months carry more weight than a single visit made shortly before you ask for a referral, so if you are at the beginning of this process, start the record now rather than later. Second, dated photographs of shoulder grooving and of a rash while it is active are worth keeping, because both are intermittent and neither may be visible on the day of your appointment.
To be clear about what this does and does not achieve: whether your case meets the Medicare Benefits Schedule criteria is a clinical determination made by your surgeon against the current item descriptors, not something a patient or a website can decide in advance. Criteria can include matters such as the presence of documented functional symptoms and the amount of tissue to be removed. A good record does not guarantee an item number - it makes sure the assessment is made on complete information rather than on what you could remember on the day.
The trade that matters: symptoms against sensation and breastfeeding
Reduction is one of the more reliably satisfying operations in this field for symptom relief - the weight comes off the shoulders and back, and most of the mechanical symptoms above are addressed directly. The honest counterweight is that two things may change, and both follow from what the operation physically does.
During a reduction the nipple and areola normally stay attached to the breast, on a pedicle - a column of underlying tissue that carries their blood supply and nerve supply with them as they are moved to a higher position. The milk ducts run through that same tissue. So the further the nipple has to travel and the more tissue is removed around it, the more of the nerve supply and duct continuity is disturbed.
The practical consequences:
- Sensation. Altered nipple sensation is common in the early months and usually improves. In some people a change is permanent, and it can be either reduced sensation or increased sensitivity.
- Breastfeeding. This surgery may affect your ability to breastfeed. Some people breastfeed successfully afterwards and others cannot, and it cannot be guaranteed either way in advance. This is the main reason it is generally advisable to wait until childbirth and breastfeeding have finished.
If either matters to you, say so explicitly at your first consultation rather than assuming it will be raised - it is part of how the operation is planned, not an afterthought.
Suitability
You may be a candidate if you are physically and mentally healthy, your breasts are fully developed, and you are experiencing discomfort or limitation because of breast size. Suitability can only be determined through consultation with a qualified health practitioner.
Points to consider before deciding:
- It is generally advisable to wait until breast development, childbirth and breastfeeding have finished, as the ability to breastfeed may be affected by this surgery.
- Changes to your breasts from pregnancy, or from significant weight loss or gain, can alter the outcome of the procedure.
- Smokers are at increased risk of complications, and stopping well before and after surgery assists healing.
- A stable weight matters, as significant weight change alters breast size and shape.
Who tends to be assessed for this operation
- People who have had large breasts since adolescence, where symptoms have been present for years and conservative measures are long exhausted.
- After pregnancy and breastfeeding, where both volume and position have changed and the family is complete.
- After significant weight loss, where the breast is emptier and lower but the skin envelope has not reduced with it - here the lift component usually does most of the work.
- Marked asymmetry, where one side is reduced substantially more than the other, or only one side is operated on.
- After breast cancer treatment, where a reduction on the unaffected side is used to match a reconstructed breast. This is a reconstructive context and is assessed differently.
What this operation does not do
It does not fill the upper part of the breast. Reduction and lift reshape and reposition what you have; they do not add volume above. Where upper fullness is also wanted, that is a conversation about a lift with implants.
It is not a weight-loss operation, and it does not treat back pain arising from other causes. Where the pain has a separate spinal or musculoskeletal cause, removing breast weight may help the load but will not treat that condition.
It does not stop the breast changing afterwards. Pregnancy, significant weight change and time continue to act on the result.
It does not avoid scars. Every version of this operation leaves scars on the breast, and the pattern is chosen to suit the correction needed, not to minimise scarring in isolation.
Preparing for surgery
- Undergo a medical evaluation and provide your full medical history, including medications, allergies and previous operations.
- Have a mammogram before surgery, and again post-operatively, to detect changes in breast tissue.
- Stop smoking well in advance, as nicotine inhibits recovery.
- Avoid aspirin, anti-inflammatory drugs and herbal supplements, which can increase bleeding.
- Arrange for someone to drive you home and stay with you for at least 24 hours.
- Prepare a comfortable area at home for your recovery.
- Bring your record of symptoms and the measures already tried to your first appointment, along with any physiotherapy or specialist letters.
The process from first enquiry to final review
- GP visit and referral. A referral is required, and it is also the point at which your documented symptoms are recorded by someone other than you.
- First consultation, with the operating surgeon - examination and measurement, discussion of the incision pattern, what reduction is realistic, and the sensation and breastfeeding trade above.
- Assessment against the current MBS criteria, where a rebate is in question, so you know before you commit whether an item number is expected to apply.
- Written quote and written risk information to take home and read.
- Cooling-off period of at least seven days after the second consultation before surgery can be booked or a deposit paid. For anyone under 18 the requirement is three months and a mandatory psychological assessment.
- Second consultation to confirm the plan and consent, and pre-operative mammography.
- Booking and payment, due four weeks before the date, and pre-admission with the hospital.
- Surgery, usually with an overnight stay, then reviews at seven to ten days, six to eight weeks, three months, six months and twelve months.
What you receive
- An itemised written quote separating the surgeon's fee, the anaesthetist's fee, hospital and theatre costs, garments and post-operative visits - and, where an item number applies, what it changes and what it does not.
- Written, procedure-specific risk information rather than a generic consent sheet.
- A supportive post-operative bra and written wound-care instructions, including scar management.
- An after-hours direct number for questions or concerns.
- A scheduled follow-up plan through to twelve months.
- Advice on post-operative mammography, since the appearance of the breast on imaging changes after a reduction and your baseline needs re-establishing.
Recovery
The first 24 hours. You may feel drowsy from the general anaesthetic. You cannot drive yourself - you need someone to drive you home and stay with you. An overnight hospital stay is common for this combined procedure.
The first weeks. Expect swelling, bruising and discomfort, which can be managed with prescribed medication. A supportive bra is worn and strenuous activity avoided during early healing. Gentle walking is encouraged to promote circulation.
Returning to activity. Most people return to work and light activities within two to three weeks, depending on the physical demands of the job. Strenuous physical activity is generally avoided for around three weeks, with a return to previous exercise routines from around six weeks.
Travel and swimming. Domestic flights are usually fine at around two weeks. Wait six to eight weeks before international or long-haul flights, and six to eight weeks before swimming.
Follow-up. You return to the clinic for your first post-operative check within a few days. Most patients are then seen at seven to ten days, six to eight weeks, three months, six months and twelve months. An after-hours direct number is provided in case you have questions or concerns.
Full recovery can take several months as swelling resolves and incision lines fade. Relief of the mechanical symptoms - the weight on the shoulders and upper back - is often noticed early, well before the breasts have settled into their final shape.
Wound care and signs of a problem
Clean your hands before touching the wound area. Clean gently with mild saline or as directed, pat rather than scrub, keep the area dry, and change dressings as advised. Do not apply ointments or creams unless prescribed.
Contact your medical team immediately if you notice increased redness or warmth around the wound, persistent or worsening pain, discharge or pus, a foul smell, or fever and chills.
The junction where the vertical and horizontal incisions meet, at the bottom of an anchor pattern, is the point under the most tension and is where delayed healing most often shows. A small area there that is slow to close is not unusual and is managed with dressings; report it rather than waiting for the next scheduled appointment.
Scarring
Wherever an incision is made there will be a scar, and the anchor pattern used for larger reductions leaves more scarring than a lollipop pattern. The horizontal incision sits in the natural fold beneath the breast, which helps conceal it. Scars mature and fade over time, though their final appearance varies between individuals.
Scarring can be reduced by not smoking, eating well, maintaining a stable weight, avoiding sun exposure to the surgical area, keeping incision sites clean and dry, limiting physical strain, and using silicone sheets or gels for scar management as directed.
Scars on the breast follow a predictable course rather than improving steadily: they are typically at their most red and raised somewhere between one and three months, and then soften and fade over the following year or more. Judging the scar at six weeks is judging it at its worst.
Risks and complications
All surgical procedures carry risks and potential complications. Because this procedure combines two operations, it carries the risks of both.
The risks for breast reduction and lift are those applicable to any major surgery, including bleeding, infection and adverse reactions to anaesthesia. Bruising, scarring and loss of sensation in the nipples are also risks to consider.
Further risks include:
- Asymmetry - the breasts may not be perfectly symmetrical in size, shape or position afterwards.
- Seroma or haematoma - collections of fluid or blood under the skin, which may require additional treatment.
- Delayed healing - wounds may take longer than usual to heal, potentially leading to tissue loss or the need for revision surgery.
- Unfavourable scarring - scars may be more prominent or heal differently than expected.
- Necrosis - uncommonly, the nipple, areolar region or breast tissue can experience tissue death, which significantly affects healing and the final result.
- Effect on breastfeeding - this surgery may affect your ability to breastfeed.
General surgical risks include swelling, pain, nerve damage, anaesthesia complications, blood clots (DVT and pulmonary embolism), psychological impact, and unsatisfactory results requiring further surgery.
Smoking deserves a specific mention here rather than a general one. The nipple survives on the blood supply carried in the pedicle, and nicotine narrows exactly those small vessels. That is why the advice to stop is firmer for this operation than for many others, and why surgeons ask about it directly.
All possible risks are explained to you during the consultation process, and you are given written information to take home. Please read our information on the risks and complications of cosmetic surgery before proceeding.
Any surgical or invasive procedure carries risks. Before proceeding you should seek a second opinion from an appropriately qualified health practitioner. The information on this page is general guidance only and cannot be used as the basis for a surgical decision - an initial consultation with a surgeon is required to make an informed decision.
Referral and cooling-off period
Since 1 July 2023, all patients are required to have a GP referral before seeing a plastic surgeon or doctor about cosmetic surgery. A valid referral is also needed if you wish to claim a Medicare rebate on medically essential surgery.
For any cosmetic surgery there is a compulsory one-week cooling-off period after your second consultation before surgery can be booked or a deposit paid.
Costs
Cost depends on the complexity of the procedure and the time required, which is determined at consultation. As a guide, breast reduction surgery ranges from $16,000 to $27,000 and breast lift surgery from $15,000 to $22,000; a combined procedure is quoted individually after assessment.
As at September 2024 and including GST, a consultation with a Specialist Plastic Surgeon is $350. After your consultation you receive a customised, no-obligation quote.
Payment for major surgery is due four weeks before the procedure. Cash, EFTPOS, direct deposit and major credit cards are accepted, with surcharges applying to cards. Independent medical finance companies are available.
Medicare and health insurance
Where the reduction component is deemed medically necessary, a Medicare rebate may be available. The relevant Medicare Benefits Schedule item number for breast reduction for symptomatic relief is 45523, and for mastopexy 45558. To qualify you must meet the strict criteria for MBS item 45520, which for reduction require evidence of functional problems such as rashes, back pain or posture issues, and you must have a valid GP referral.
Item numbers are updated periodically, so confirm the current numbers and criteria with your surgeon and on MBS Online. Without meeting the criteria, the surgery is considered elective and no rebate applies.
If you are eligible for an item number and hold the right level of cover, your health insurer may subsidise part of the cost. We are not a no-gap provider, so a significant out-of-pocket payment remains.
Two things are worth understanding about what a rebate is actually worth. A Medicare benefit is a fixed schedule amount attached to the item number, not a percentage of what you are charged, so it does not scale with the fee. And where a lift is performed alongside a reduction, the two components may be treated differently - the functional component may attract an item number while the rest does not. Ask for the out-of-pocket figure with the rebate already allowed for, rather than a gross fee and a rebate quoted separately.
Where surgery is performed
Our surgeons operate at accredited private hospitals around Melbourne, including Masada Private Hospital (St Kilda East), Epworth Geelong (Waurn Ponds), St Vincent's Werribee, Sir John Monash Private Hospital (Clayton), Peninsula Private Hospital (Langwarrin) and Linacre Private Hospital (Hampton).
Common questions about breast reduction and lift
Why do the two procedures usually go together?
A reduction removes volume and weight, but where the breast has also lost position — the nipple resting below the breast crease, or the skin stretched by the weight it has carried — reducing volume alone can leave the breast lower and less supported than intended. Adding a mastopexy repositions the nipple and areola and removes excess skin at the same time. The incision patterns used for reduction (anchor or lollipop) are also the same patterns used for a lift.
Will I definitely need the lift component?
Your surgeon assesses at consultation whether it is needed in your case.
What does the combined procedure address?
Back, neck and shoulder pain associated with breast size and weight; skin irritation and rashes beneath the breast crease; limitations on physical activity and exercise; indentations from bra straps; stretched skin and nipples resting below the breast crease with enlarged areolas; size, shape and position together; and asymmetry between the breasts.
What should I bring to my first appointment?
A written, dated record of your symptoms - shoulder grooving, neck and back pain, rash in the fold, activities you have given up, sleep and bra-fitting problems - and an account of what you have already tried, such as a professionally fitted bra, physiotherapy, pain relief and topical treatment. Bring any physiotherapy or specialist letters. Dated photographs of grooving and of a rash while it is active are worth keeping, because both are intermittent and may not be visible on the day.
Does having good records mean I will get a rebate?
No. Whether your case meets the MBS criteria is a clinical determination made by your surgeon against the current item descriptors. A good record does not guarantee an item number; it makes sure the assessment is made on complete information rather than on what you could recall on the day.
Will I still be able to breastfeed?
This surgery may affect your ability to breastfeed. The nipple is moved on a pedicle of tissue that carries its blood supply, nerve supply and the milk ducts, so the further it travels and the more tissue is removed, the more duct continuity is disturbed. Some people breastfeed successfully afterwards and others cannot, and it cannot be guaranteed either way. It is generally advisable to wait until childbirth and breastfeeding have finished.
Will I lose sensation in my nipples?
Altered nipple sensation is common in the early months and usually improves. In some people a change is permanent, and it can be either reduced sensation or increased sensitivity. Loss of sensation in the nipples is a recognised risk of this surgery.
Will I stay in hospital overnight?
An overnight hospital stay is common for this combined procedure, because it is more extensive than either component alone.
Which incision pattern will be used?
Most commonly an anchor pattern where there is significant enlargement and sagging, or a lollipop pattern for moderate correction. The anchor pattern leaves more scarring, though the horizontal incision sits in the natural fold beneath the breast, which helps conceal it.
Can the areola be reduced too?
Yes — the areola is reduced if required and the nipple repositioned during the same operation.
Should I wait until after having children?
It is generally advisable to wait until breast development, childbirth and breastfeeding have finished, as the ability to breastfeed may be affected by this surgery, and changes from pregnancy can alter the outcome.
Will weight change affect the result?
Yes. Significant weight loss or gain alters breast size and shape and can alter the outcome of the procedure, so a stable weight matters.
Do I need a mammogram beforehand?
Yes — have one before surgery, and again post-operatively, to detect changes in breast tissue. The appearance of the breast on imaging changes after a reduction, so the post-operative study re-establishes your baseline.
Why is smoking singled out for this operation?
Because the nipple survives on the blood supply carried in the pedicle of tissue it is moved on, and nicotine narrows exactly those small vessels. That is why the advice to stop is firmer here than for many other procedures.
How long is the recovery?
Most people return to work and light activities within two to three weeks, depending on the physical demands of the job. Strenuous physical activity is generally avoided for around three weeks, with a return to previous exercise routines from around six weeks. Full recovery can take several months as swelling resolves and incision lines fade, though relief of the weight on the shoulders and upper back is often noticed early.
When can I fly or swim?
Domestic flights are usually fine at around two weeks. Wait six to eight weeks before international or long-haul flights, and six to eight weeks before swimming.
My scar looks worse at two months than it did at two weeks. Is that normal?
Yes. Scars on the breast are typically at their most red and raised somewhere between one and three months, then soften and fade over the following year or more. Judging a scar at six weeks is judging it at its worst. Report anything that is opening, discharging or increasingly painful rather than waiting.
Does combining two procedures increase the risks?
It carries the risks of both. Those include the risks of any major surgery — bleeding, infection and adverse reactions to anaesthesia — plus bruising, scarring, loss of sensation in the nipples, asymmetry, seroma or haematoma, delayed healing, unfavourable scarring, and uncommonly necrosis of the nipple, areolar region or breast tissue.
What does it cost?
A combined procedure is quoted individually after assessment. As a guide, breast reduction surgery ranges from $16,000 to $27,000 and breast lift surgery from $15,000 to $22,000. As at September 2024 and including GST, a consultation with a Specialist Plastic Surgeon is $350, and payment for major surgery is due four weeks before the procedure.
Which Medicare item numbers apply?
45523 for breast reduction for symptomatic relief, and 45558 for mastopexy. To qualify you must meet the strict criteria for MBS item 45520 — for reduction, evidence of functional problems such as rashes, back pain or posture issues — and hold a valid GP referral. Without meeting the criteria the surgery is considered elective and no rebate applies. We are not a no-gap provider.
How much will the rebate actually reduce my bill?
Less than people expect. A Medicare benefit is a fixed schedule amount attached to the item number, not a percentage of the fee charged, and where a lift accompanies a reduction the components may be treated differently. Ask for the out-of-pocket figure with the rebate already allowed for.
Can I decide based on this page?
No. The information here is general guidance only and cannot be used as the basis for a surgical decision — an initial consultation with a surgeon is required to make an informed decision.
Related procedures
If you are considering only one component, see breast reduction or breast lift. Where upper fullness is also wanted, see breast lift with implants. See all breast surgery procedures, or the Me Clinic team.
Images on This Page
-
https://www.meclinic.com.au/wp-content/uploads/2024/03/meclinic-logo.png
Me Clinic
-
https://www.meclinic.com.au/wp-content/uploads/2022/02/call.png
call
-
https://www.meclinic.com.au/wp-content/uploads/2024/05/breast-reduction-and-lift-melbourne-1024x512.png
An image design of the benefits of a breast reduction and lift. This combines a breast reduction and breast lift to decrease breast size while restoring shape and contour.
-
https://www.meclinic.com.au/wp-content/uploads/2024/05/breast-reduction-and-lift-1-1024x512.png
An image comparison of before and after a breast reduction and lift. Highlights restoration in sagging breasts and proportionate breast size.
-
https://www.meclinic.com.au/wp-content/uploads/2024/05/breast-reduction-and-lift-300x300.png
An image illustrating a breast reduction and lift potential to reduce and shape the breasts.
-
https://www.meclinic.com.au/wp-content/uploads/2022/02/malvern-map-thumb.jpg
(no alt text)
-
https://www.meclinic.com.au/wp-content/uploads/2024/02/acps.png
Australian Society Of Plastic Surgeons
-
https://www.meclinic.com.au/wp-content/uploads/2024/02/racs.png
Royal Australian College Of Surgeons
-
https://www.meclinic.com.au/wp-content/uploads/2024/02/fracs.png
fracs
-
https://www.meclinic.com.au/wp-content/uploads/2024/02/isaps.png
isaps
-
https://www.meclinic.com.au/wp-content/uploads/2024/02/cpca.png
(no alt text)
-
https://www.meclinic.com.au/wp-content/uploads/2022/02/auscop.png
College
-
https://www.meclinic.com.au/wp-content/uploads/2022/02/amav.png
AMA
-
https://www.meclinic.com.au/wp-content/uploads/2022/03/home-conctact-tab.jpg
(no alt text)
-
https://bat.bing.com/action/0?ti=56339805&Ver=2&mid=e45dbd1a-d6ae-457d-829e-2f8e60b5efdc&bo=1&sid=cb107870ac3811f1bafe35c330589c9f&vid=cb109dd0ac3811f19008c75b668d16cb&vids=1&msclkid=N&pi=918639831&lg=en-US&sw=1280&sh=720&sc=24&tl=Breast%20Reduction%20and%20Lift%20-%20restore%20breast%20proportion%20%26%20drooping&p=https%3A%2F%2Fwww.meclinic.com.au%2Fbreast-surgery%2Freduction-and-lift%2F&r=<=2082&evt=pageLoad&sv=2&cdb=AQAQ&rn=388392
(no alt text)